Strength Testing: A Guide to Manual Muscle Testing and Dynamometry
Treatment Guidelines
MMT grades explained. How to perform manual muscle testing, and when dynamometry gives more objective, repeatable strength data.
Learn the manual muscle testing grades (0–5, including plus and minus grades), how to perform MMT, and when to use dynamometry for objective, repeatable strength measurement.
In the rehab field, practitioners have a variety of tools with which they can quantify strength. One of these tools, known as MMT or manual muscle testing, is a low-tech method which relies on a somewhat subjective interpretation by the clinician. Another method is dynamometry, which uses a range of equipment to more objectively assess a patient’s strength.
Both methods have their potential benefits, and their potential downsides. In this post, we’ll take a look at MMT and dynamometry to provide clinicians with an informational guide on this important subject.
At a glance: Manual muscle testing (MMT) grades strength on a 0–5 scale based on whether a muscle can contract, move against gravity, and hold against the examiner’s resistance. It is fast and needs no equipment, but it is less sensitive to mild-to-moderate deficits. Dynamometry measures force as a number, which makes side-to-side comparisons and progress tracking more precise.
A Brief History of MMT
MMT grading was developed in the early 20th century, when orthopedic surgeon Robert Lovett and physical therapist Wilhelmine Wright used gravity and manual resistance to grade weakness in patients with polio. From there, the method was refined to enable different practitioners to get as accurate an assessment of a patient’s strength as possible. The technique was further expanded for use on other patients, such as those who had suffered neuromuscular injuries or were experiencing weakness for any reason.
What is Manual Muscle Testing (MMT)?
Manual Muscle Testing (MMT) is the most widely used method for documenting muscle strength deficits in rehabilitation. It is a standardized clinical procedure where a therapist applies resistance to a patient’s limb to grade their strength on a specific scale.
Unlike strength training, which builds muscle, MMT is a diagnostic tool used to:
- Identify Weakness: Pinpoint specific muscles or muscle groups that are underperforming due to injury, atrophy, or neurological impairment.
- Establish a Baseline: Create a starting point for therapy to measure progress against.
- Localize Lesions: In neurology, patterns of weakness found during MMT can help localize nerve damage (e.g., differentiating a peripheral nerve injury from a spinal root injury).
While simple in concept, MMT requires a high degree of skill. The clinician must understand line-of-pull, proper stabilization, and anatomy to isolate the target muscle and avoid “compensation” (where strong muscles take over for weak ones). Because it relies on the therapist’s perception of effort, it is often described as a “subjective” measure, though standardized grading scales (like the MRC, or Oxford, scale) attempt to make it as objective as possible.
How to Perform MMT Like a Pro: Techniques and Best Practices
Because MMT relies on the clinician’s own muscular strength, body mechanics are paramount. The therapist should ensure that they position themselves in such a way so as to minimize stress on their own joints, while also being mindful of the patient’s comfort and positioning.
MMT is a useful tool for degenerative diseases which can progress quickly (both in terms of improvement and worsening). By frequently monitoring a patient’s strength from day to day, practitioners can gather meaningful data on the progression of conditions such as ALS, muscular dystrophy, or spinal cord injuries to name a few.
Guide to Performing MMT
There are a few key principles to keep in mind when it comes to MMT. Namely, the therapist must ensure that the patient:
- Has adequate range of motion in the joint of interest.
- Is able to get into a position where they can activate the muscle, moving the limb against the force of gravity.
For instance, when testing the strength of the biceps brachii. The following steps should be followed:
- Have the patient seated comfortably, while the therapist stands.
- Ensure that the patient has adequate passive and active range of motion of the elbow joint.
- Assuming that range of motion is normal, have the patient fully flex their elbow, with the forearm supinated.
- The patient is instructed to maintain this position, while the therapist attempts to pull the elbow into extension and rotate the forearm into pronation. The therapist’s other hand should stabilize the patient’s shoulder.
- The patient’s muscle strength is then graded, according to one of the systems described in the next section.
MMT Grades: The 0–5 Scale Explained
Most clinicians grade MMT on the 0–5 Medical Research Council (MRC) scale, which is often called the Oxford scale. The two names describe the same system. Many clinics add plus (+) and minus (−) modifiers, following the Kendall or Daniels and Worthingham conventions, to capture changes between whole grades.1,2
| Grade | Kendall term | What the clinician observes |
|---|---|---|
| 5 | Normal | Full range of motion against gravity; holds the test position against maximal resistance |
| 4+ | Good+ | Full range against gravity; holds against moderate-to-strong resistance |
| 4 | Good | Full range against gravity; holds against moderate resistance |
| 4− | Good− | Full range against gravity; holds against less-than-moderate resistance |
| 3+ | Fair+ | Full range against gravity; holds against minimal resistance |
| 3 | Fair | Full range against gravity with no added resistance |
| 3− | Fair− | Moves against gravity through more than half, but not all, of the range |
| 2+ | Poor+ | Moves through less than half the range against gravity (or completes the gravity-minimized range against slight resistance, depending on the convention used) |
| 2 | Poor | Full range of motion with gravity minimized |
| 2− | Poor− | Partial range of motion with gravity minimized |
| 1 | Trace | Visible or palpable contraction with no joint movement |
| 0 | Zero | No visible or palpable contraction |
Plus and minus definitions vary slightly between grading conventions, so document which system your clinic uses and apply it consistently across clinicians. Grades above 3 depend on how much resistance the examiner applies, which is why MMT becomes less sensitive in the 4 to 5 range.
Make vs. Break MMT: Key Differences and When to Use Each
Under the umbrella of MMT, there are “make” tests and “break” tests. Most therapists will use these tests with fluidity, selecting one or the other depending on the specific nature of the patient’s condition.
The Make Test
The make test involves holding constant resistance against the patient’s fully contracted muscle. This allows the therapist to determine the patient’s isometric strength.
The Break Test
The break test involves the therapist applying more and more resistance against the patient’s fully contracted muscle in an attempt to push them out of the position. This tests isometric strength in addition to eccentric strength of the involved muscle.
Why Objective Strength Testing Matters
Having accuracy in data collection is important in all fields. For this reason, it is best to not rely solely on subjective measures, such as manual muscle testing, when assessing a patient’s strength. Better data during examination and evaluation supports better clinical decisions.
The evidence supports this caution. In a study of 107 rehabilitation inpatients, MMT’s sensitivity for detecting 15–30% side-to-side differences in knee extension force (measured with handheld dynamometry) never exceeded 75%, and its diagnostic accuracy never exceeded 78%.3 In other words, a “normal” grade does not rule out a clinically meaningful deficit. For a deeper look, see our guide to objective strength testing.
The Power of Dynamometry: Precision Testing for Optimal Results
Dynamometers provide a numerical value for strength which is generally considered both reliable and valid. MMT is faster and needs no equipment, but dynamometry offers greater precision, better sensitivity to change, and data that can be compared across visits and clinicians.
As long as the equipment is well-maintained and the proper testing protocols are followed, clinicians can obtain consistent, repeatable measurements of the patient’s strength at each visit. This is crucial for baseline measurements, discharge planning, and for generally assessing the patient’s response to treatment. For more on test types, see isometric testing methods and isokinetic vs. isotonic vs. isometric approaches.
Fixed Dynamometers: Stabilized, Repeatable Strength Assessment
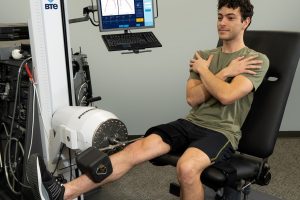
A fixed dynamometer is mounted to a stable frame so neither the device nor the clinician moves during the test. Fixed isokinetic dynamometers are the reference standard researchers use to validate other strength measures.4 Clinical systems such as the PrimusRS bring this stabilized, repeatable testing into everyday practice, so clinicians can test, treat, and re-test on the same system.
Portable Evaluation Systems: Objective Testing On Site
When testing has to happen outside the clinic, such as at a job site, a training facility, or a satellite location, portable evaluation systems bring standardized strength testing to the patient. BTE’s EVJ supports objective strength and range-of-motion testing, and the Evaluator provides portable, objective strength testing.
Handheld Dynamometers: Pros, Cons, and When to Use Them
These portable devices are extremely convenient for clinicians and easy to use for patients. However, they may be less reliable when used for testing certain body areas, and repeatability can vary when compared to fixed assessment devices. These are great tools to use throughout a patient’s rehab program for many conditions, especially when a fixed dynamometer is unavailable. Handheld grip dynamometers are a common example; see BTE’s grip strength dynamometer options.
The “Therapist Strength” Limitation
Handheld Dynamometers (HHD) are a major upgrade over MMT, but they have a distinct physical limitation: You.
In order to get an accurate reading, the therapist must be stronger than the muscle group being tested. If a therapist cannot hold the device completely still against the patient’s force (stabilization), the reading will be artificially low.5 This is particularly problematic when testing strong muscle groups like the quadriceps or plantar flexors in athletic populations. This matters most in return-to-sport testing, where small side-to-side differences influence clearance decisions.
Fixed Dynamometers eliminate this variable by removing the clinician from the force equation entirely, ensuring the measurement reflects the patient’s true maximum output, not the therapist’s maximum resistance.
Research Comparing Fixed, Portable, and Handheld Tools
Research on strength testing methods points to a few consistent findings:
- MMT is reliable but not very sensitive. A systematic review found substantial to almost perfect agreement for most muscle actions tested, but MMT is less able to detect mild-to-moderate deficits than instrumented testing.3,6
- Handheld dynamometry compares well with isokinetic testing when protocols are controlled. A systematic review of 19 studies found minimal differences between handheld and isokinetic measurements, supporting handheld devices as reliable and valid in clinical settings.4
- Stabilization is the main limitation of handheld devices. Tester strength influences handheld readings, especially for strong muscle groups. This is where belt stabilization or fixed systems add the most value.5
The table below summarizes how the main methods compare in day-to-day practice.
| Method | Output | Strengths | Limitations | Best suited for |
|---|---|---|---|---|
| Manual muscle testing | 0–5 grade | Fast; no equipment; useful for screening and very weak muscles | Subjective; less sensitive above grade 3; hard to compare across clinicians | Screening; neurological exams; grades 0–3 |
| Handheld dynamometry | Force (lb, kg, or N) | Portable, affordable, numeric | Depends on tester strength and stabilization | Routine testing of most muscle groups |
| Portable evaluation systems | Force and ROM, with reports | Standardized protocols; on-site testing; documentation | Less stabilization than a fixed system | Job-site, outreach, and multi-location testing |
| Fixed dynamometers | Force or torque, with reports | Stabilized; repeatable; independent of tester strength | Larger footprint and higher cost | Strong patients and athletes; return-to-work and return-to-sport testing |
Choosing the Right Strength Testing Method
Which strength testing method is right for your practice? This will depend on a variety of factors. If you need extremely accurate data, and your budget permits, you might lean toward a fixed dynamometer or a portable evaluation system. If your practice requires more field work and you need less cumbersome tools (and are willing to sacrifice some potential accuracy in data collection), you may opt for a handheld device.
When investing in strength testing equipment, the “best” tool depends entirely on your specific clinical population and facility goals. Whether you are considering a simple handheld unit or a comprehensive fixed system, evaluate your purchase based on these three critical factors:
- Stabilization and Repeatability
This is the most important factor for data accuracy.
- Handheld Considerations: If your clinic treats high-level athletes or strong industrial workers, a handheld dynamometer (HHD) may not be sufficient. If the patient is stronger than the therapist, the reading may underestimate the patient’s true strength. Look for HHDs that come with belt-stabilization straps to mitigate this issue.
- Fixed System Considerations: For research centers and high-performance clinics, fixed systems offer greater stabilization. By removing the therapist from the physical equation, measurements taken today are directly comparable to ones taken next month, regardless of which staff member performs the test.
- Workflow Efficiency and Software
Advanced technology is useless if it creates a bottleneck in your clinic schedule.
- Data Integration: Does the device export data easily to your EMR, or will you have to manually type numbers into a computer?
- Report Generation: Look for systems that generate automatic, patient-friendly reports. A graphical report that visualizes strength deficits is a powerful tool for patient education and compliance.
- Patient Population and Strength Range
Match the tool to the patients you test most often.
- Weak or neurologically involved patients: MMT remains useful where patients cannot produce measurable force, and handheld devices capture change well in the lower strength ranges.
- Strong athletes and industrial workers: Choose stabilized options (belt-stabilized handheld devices or fixed systems) so readings reflect the patient’s output, not the tester’s.
- Mixed caseloads: A combination often works best, with MMT for screening and instrumented testing for baseline, progress, and discharge decisions.
Peruse our testing products and choose the right physical or occupational therapy assessment tools for your practice.
Billing and Reimbursement: The Financial Side of Strength Testing
Moving from subjective MMT to objective dynamometry doesn’t just improve clinical care; it can also support a more robust billing strategy. While MMT is typically bundled into a standard evaluation, objective testing opens the door for specific performance-based codes.
Understanding CPT 97750
The most relevant code for objective strength analysis is CPT 97750 (Physical Performance Test or Measurement).
- When to use it: This code is distinct from therapeutic exercise. It is used when you are performing a specific test that produces a written report and data analysis to guide the plan of care.
Payers and auditors look closely at claims for “lack of progress.” Subjective notes (e.g., “Patient strength is 4/5”) are often deemed insufficient to justify continued therapy.
A dynamometry report stating, “Patient demonstrates a 25% strength deficit in the involved shoulder compared to the uninjured side,” provides clear, quantitative support for medical necessity. This level of documentation can help reduce claim denials and support extended plans of care.
Manual Muscle Testing FAQs
What does 4/5 muscle strength mean?
A 4/5 grade means the muscle moves through its full range against gravity and holds against moderate, but not maximal, resistance. It indicates mild weakness. Because “moderate” depends on the examiner, a 4/5 grade can hide deficits that dynamometry would quantify.
What is the difference between 3− and 3+ in MMT?
A 3− muscle moves against gravity through more than half, but not all, of its range. A 3+ muscle completes the full range against gravity and holds against minimal resistance. Exact definitions vary slightly by grading convention, so document which system your clinic uses.
Are the Oxford and MRC scales the same?
Yes. In clinical practice, the Oxford scale and the Medical Research Council (MRC) scale refer to the same 0–5 grading system. Differences come mainly from how clinics apply plus and minus modifiers.
How reliable is manual muscle testing?
MMT can be reliable: a systematic review found substantial to almost perfect agreement for most muscle actions tested.6 The bigger limitation is sensitivity. MMT often misses mild-to-moderate deficits, particularly at grades 4 and 5.3
When should I use a dynamometer instead of MMT?
Use dynamometry when you need a number: to establish a baseline, track progress, compare sides, document medical necessity, or support return-to-work and return-to-sport decisions. MMT remains useful for quick screening and for very weak muscles.
Does handheld dynamometry need stabilization?
For strong muscle groups, yes. If the tester can’t hold the device steady against the patient’s force, the reading will underestimate strength.5 Belt stabilization or a fixed system helps keep measurements consistent between visits and clinicians.